
Do You Need a 3T MRI for a Knee Injury?
Learn when 3T knee MRI can help for cartilage, meniscus, ACL, and subtle bone injuries, and when X-ray, 1.5T MRI, or existing scans are enough.
Key Takeaways
- 3T knee MRI is most useful when fine cartilage, meniscus, ligament, or marrow detail changes decisions
- X-ray is still the first test for many acute knee injuries and arthritis questions
- A dedicated knee coil and protocol can matter more than magnet strength alone
- Repeating a clear recent knee MRI just to get 3T can waste money
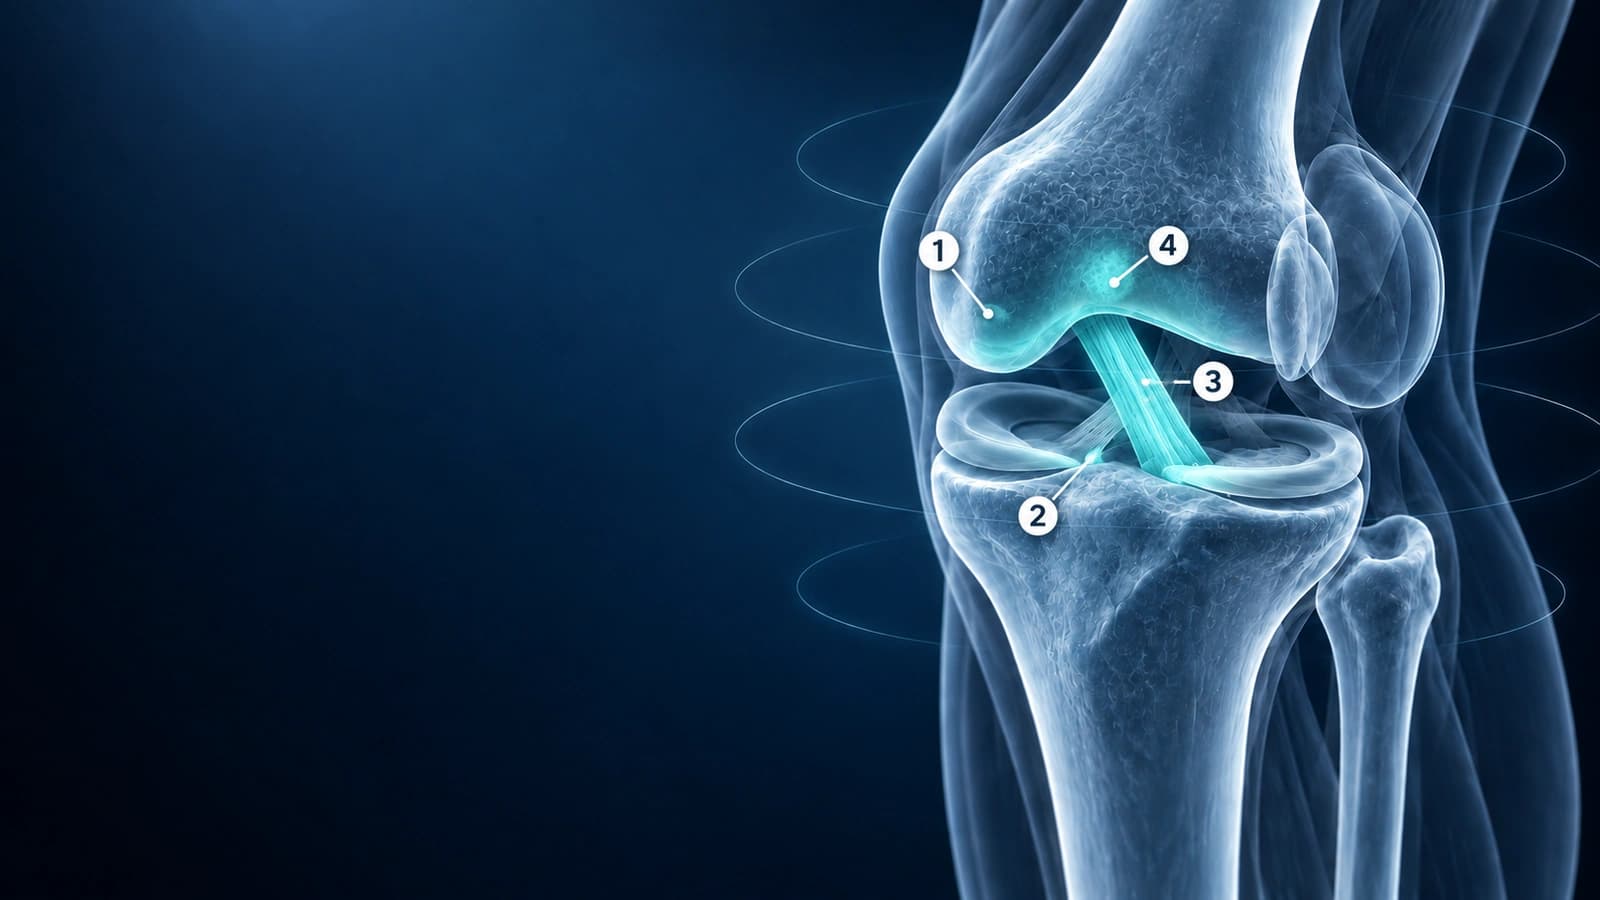
A 3T knee MRI can add detail for cartilage surfaces, subtle meniscus tears, partial ACL fiber injuries, bone marrow edema, and osteochondral lesions. It is not automatically the best first scan for every painful knee.
Use this guide before paying extra for a premium knee MRI. The right choice depends on the clinical question, the coil, the slice thickness, and whether an existing scan already answers what your orthopedist needs.
Quick Answer: When 3T Knee MRI Is Worth Asking About
Ask about 3T when the decision depends on fine cartilage detail, small partial ligament fibers, a subtle meniscus root or ramp lesion, an osteochondral defect, or persistent pain after ordinary imaging. Do not pay for 3T just because it sounds stronger if the question is a clear fracture, routine osteoarthritis grading, or a knee sprain that is already improving.
When 3T Can Add Value for Knees
- Cartilage mapping questions in patellofemoral or tibiofemoral cartilage loss
- Small meniscus root, ramp, radial, or recurrent tear questions after prior surgery
- Partial ACL, PCL, MCL, or posterolateral corner detail when management may change
- Osteochondral defects, bone bruises, and marrow edema that are hard to see on X-ray
When You Probably Do Not Need 3T
- First imaging after trauma when X-ray is needed to check fracture or alignment
- Routine osteoarthritis staging where weight-bearing X-rays answer the practical question
- A complete ACL tear or displaced fracture that is already clear on existing imaging
- Avoid repeat scanning when a recent 1.5T knee MRI already matches the exam and report
Protocol Matters More Than the Tesla Number Alone
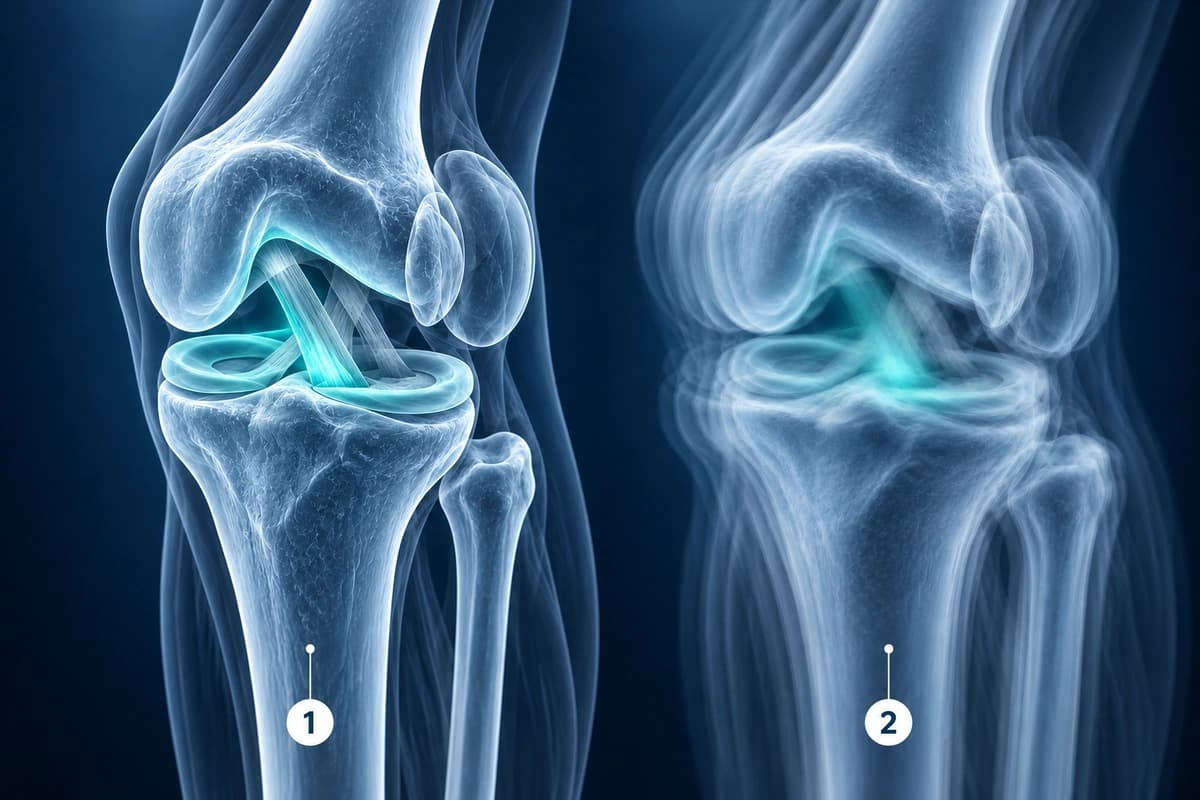
A dedicated knee coil, thin slices, the right planes, and a musculoskeletal radiologist can matter more than magnet strength by itself. A rushed 3T scan with motion blur can be less useful than a well-planned 1.5T MRI. For broader imaging choices, compare this with our MRI vs X-ray guide.
Frequently Asked Questions
Is 3T MRI always better for knee pain?
No. 3T can provide more signal and finer detail, but it only helps when the protocol, coil, and clinical question are right. X-ray, exam findings, or a good 1.5T MRI may be enough for many knee problems.
Should I pay extra for 3T MRI for a meniscus tear?
Ask if the surgeon needs fine detail such as root tear, ramp lesion, small radial tear, or re-tear after surgery. If a standard MRI already shows the tear clearly, 3T may not change treatment.
Can 3T knee MRI replace X-ray?
Usually no. X-ray is still better for weight-bearing alignment, joint-space narrowing, many fractures, and routine osteoarthritis staging. MRI adds soft-tissue and marrow detail when that detail affects care.
Sources
- Van Dyck P, Vanhoenacker FM, Lambrecht V, et al. Prospective comparison of 1.5 and 3.0-T MRI for evaluating the knee menisci and ACL. J Bone Joint Surg Am. 2013;95(10):916-924.
- Oei EH, Nikken JJ, Verstijnen AC, et al. MR imaging of the menisci and cruciate ligaments: a systematic review. Radiology. 2003;226(3):837-848.
- Expert Panel on Musculoskeletal Imaging; Taljanovic MS, Chang EY, et al. ACR Appropriateness Criteria Acute Trauma to the Knee. J Am Coll Radiol. 2020;17(5S):S12-S25.
- Expert Panel on Musculoskeletal Imaging; Bateni CP, Ha AS, et al. ACR Appropriateness Criteria Chronic Knee Pain: Update 2026. J Am Coll Radiol. 2026;23(8):1799-1809.
Related Articles
Learn to understand your knee MRI report, common sequences, and what key findings mean for your diagnosis.
Knee MRI cost ranges, what affects price (3T vs 1.5T, contrast, hospital vs imaging center), insurance coverage, and how to lower your out-of-pocket cost.
Compare MRI and X-ray imaging, understand when each is appropriate, radiation considerations, cost, and diagnostic capabilities.
Related Conditions
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer